

Reasons I Dislike Using Silicone in the Nose #4 (Nasal Implant Removal / Revision Rhinoplasty / Deviated Nose)

Silicone implants remain, in Asia and
It is the most widely used material worldwide for raising the dorsum.
The association is so direct that "rhinoplasty" brings "silicone" to mind.
In Asia in particular, when it comes to "rhinoplasty," both doctors and patients
I often see it taken for granted that silicone will be used.
In rhinoplasty, this is a highly inappropriate and even dangerous notion.
For example, even in rhinoplasty whose goal is not to raise the bridge, such as dorsal hump correction or deviated nose surgery,
I see many patients in whom silicone was used even in such rhinoplasty.
When such patients come for a revision consultation and are examined, we often find that the silicone
In many cases it has been of no help at all and has instead caused side effects.
In fact, having seen many side effects from silicone and artificial materials over years of revision rhinoplasty,
I had long wanted to organize this systematically and present it someday.
So today, under the title "Reasons I Dislike Using Nasal Silicone (in Rhinoplasty)!",
I have prepared case studies on each of the side effects.

Side Effects Caused by Silicone Implants After Rhinoplasty
- 1. Silicone breaking through the skin of the nasal tip or the mucosa inside the nose due to physical pressure
- 2. Acute or chronic inflammation caused by silicone or artificial materials used with it
- 3. Contracture caused by capsule formation and inflammation
- 4. Silicone that repeatedly shifts even after corrective surgery
- 5. Tip cartilages deformed by silicone that extends to the nasal tip
- 6. Calcium deposits on the silicone making the dorsum protrude unevenly
- 7. Dorsal skin thinning and turning red, with the silicone showing through
- 8. Recurrent hematoma in the dorsum (inside the silicone capsule)
The probability of side effects after rhinoplasty with a silicone implant differs somewhat
among the published papers, ranging fairly widely from 4-36%.
The difference arises from when the side effects were diagnosed.
The most common side effects are contracture (34.8%), implant deviation (30.1%),
inflammation (10.1%), skin thinning (19.9%), and extrusion through a perforation (5%).
This case study will continue as a series of 8 parts, and we hope you will follow it.

Silicone That Repeatedly Shifts
Even After Corrective Surgery (Shifted Silicone Implant)
To have their shifted silicone straightened, some of these patients
were told that simply moving the silicone back to the center would be enough,
and I have seen quite a few who underwent surgery repeatedly as a result.
However, the silicone soon shifts again, and in many cases contracture gradually develops as well.
This is because even if the capsule surrounding the silicone is torn to create a new pocket
and the silicone is placed exactly in the midline, it slides back
into the space where the existing capsule lies.
If the capsule is removed and the pocket is made wide, the pocket is larger than the silicone,
so the silicone easily becomes unstable and migrates.
Once silicone has shifted like this, it is almost impossible to center it by moving the silicone alone,
so it needs to be removed, or the silicone and capsule removed and replaced with acellular dermal matrix.

PH
Woman in her 40s. After augmentation rhinoplasty with a silicone implant at another clinic 6 years earlier, her nose became crooked,
and 6 months later she had one surgery to straighten it by repositioning the implant alone, but it became crooked again.
P/E
The dorsum, tip, and columella were all crooked.
OP
An open approach was used to remove the silicone and capsule, a columellar strut was re-established to straighten the bent
tip cartilages, and acellular dermal matrix was placed on the dorsum so that it extended only to just above the tip.

The crooked nose was straightened, and the height and shape of the bridge became natural and attractive.
The tip became natural.
PH
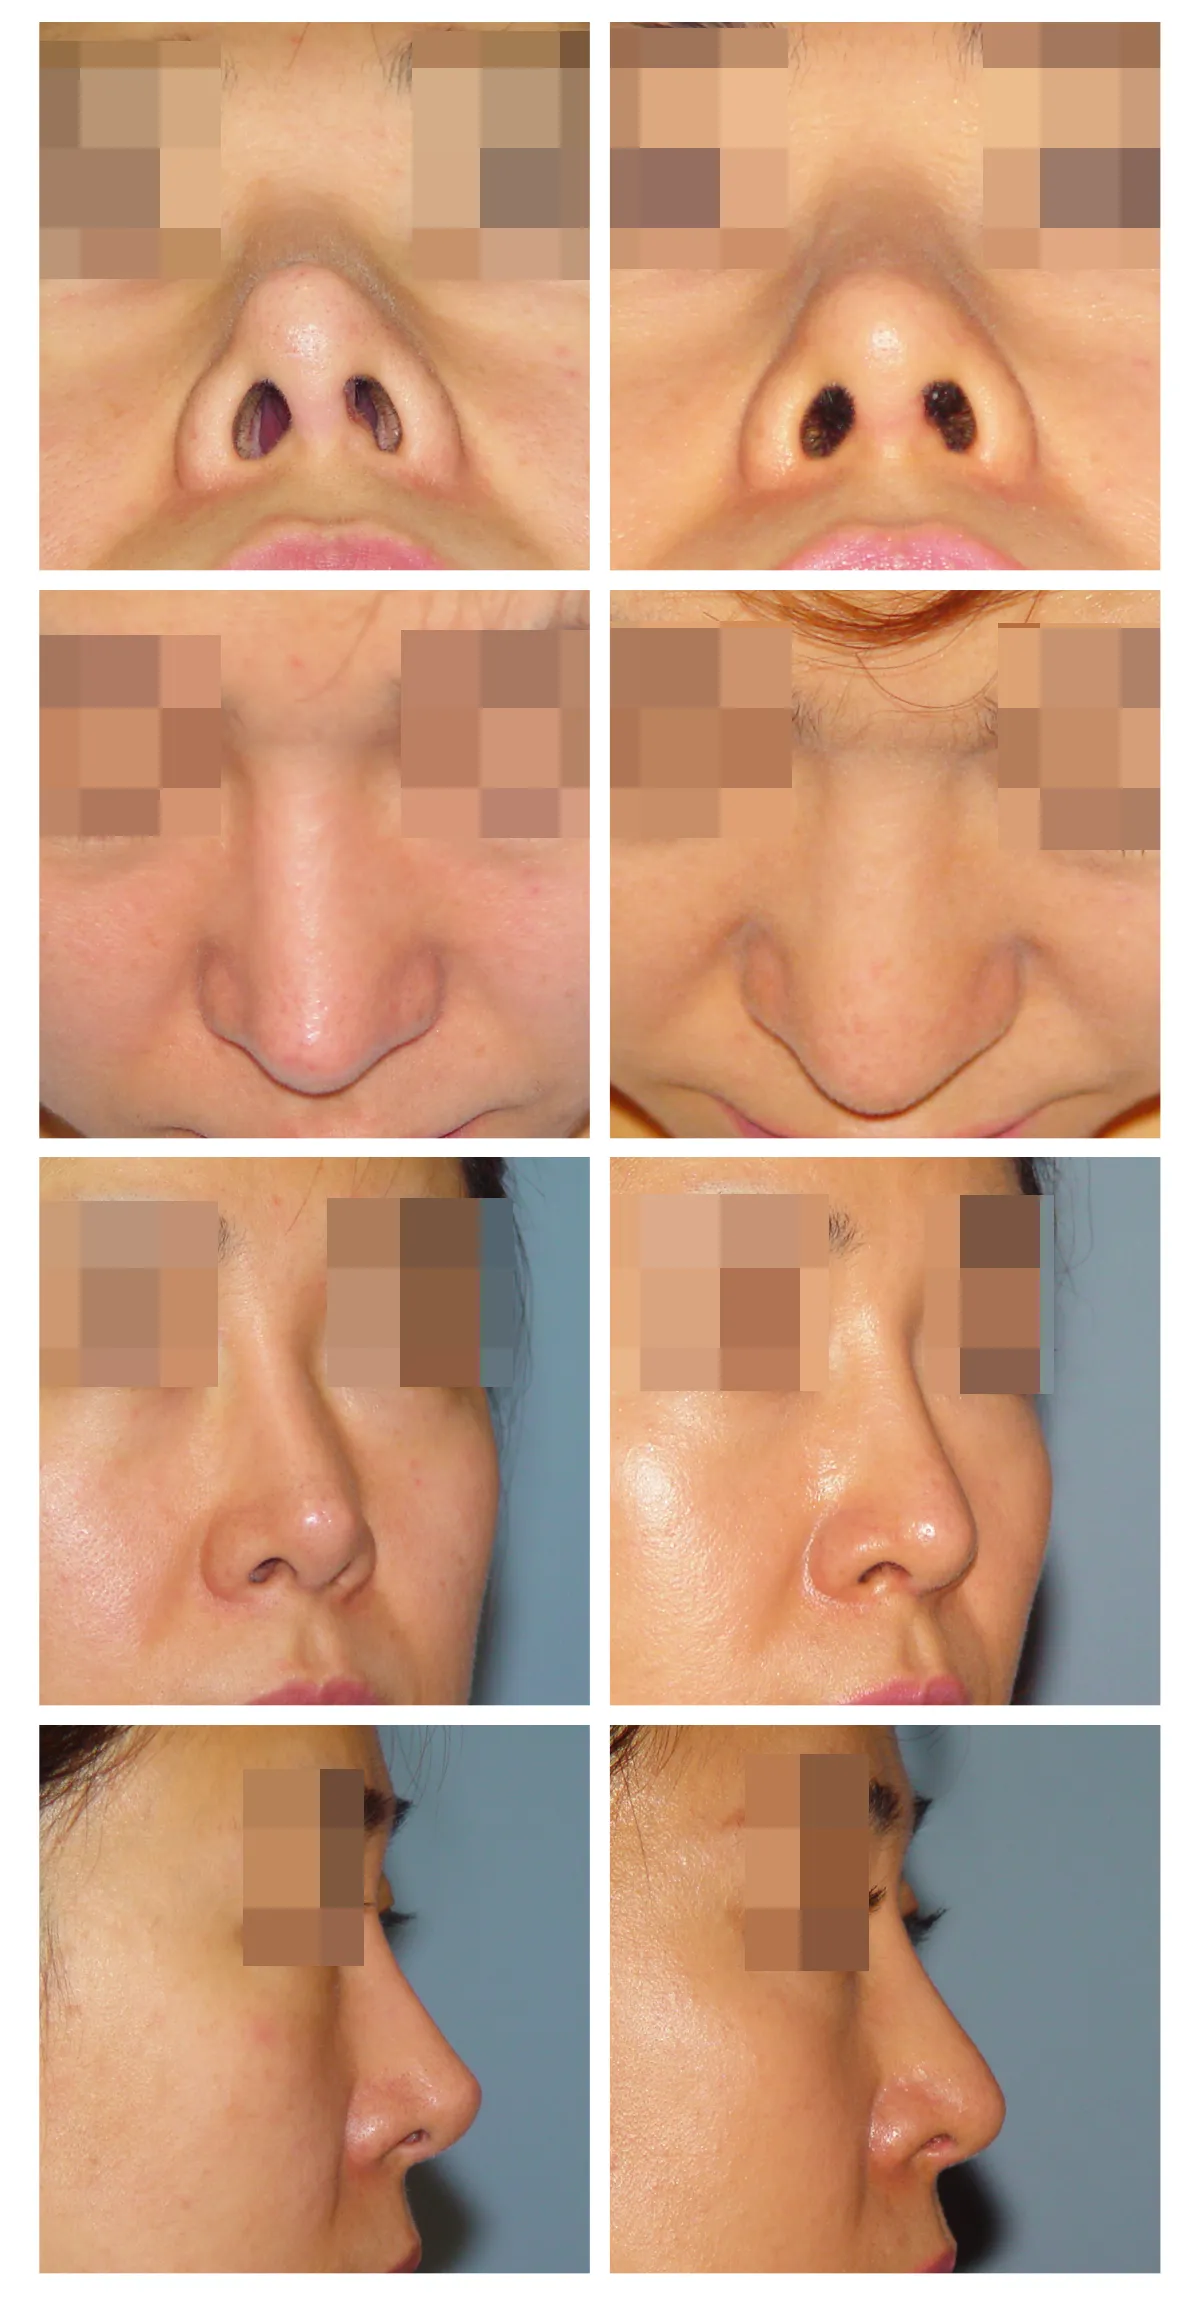
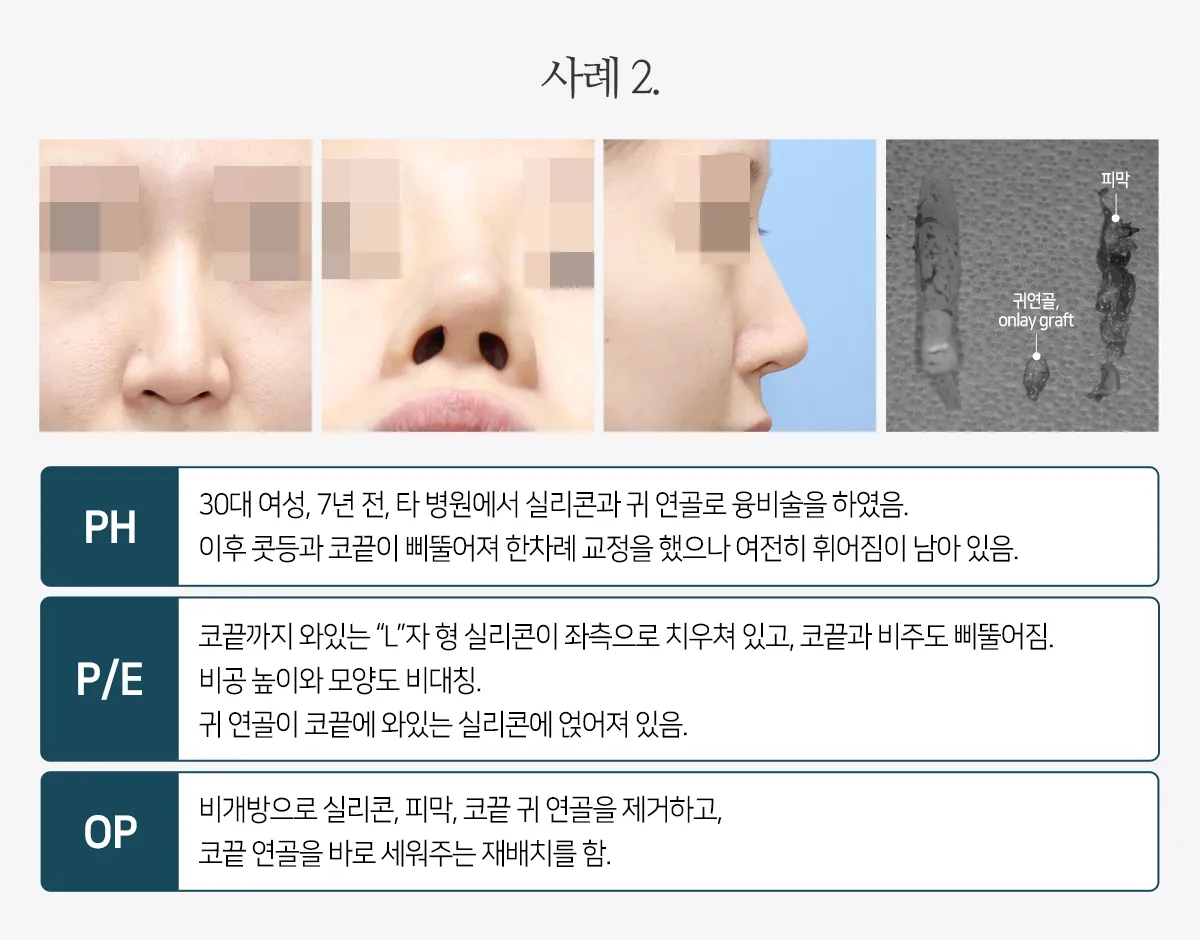
Woman in her 30s. She had augmentation rhinoplasty with silicone and ear cartilage at another clinic 7 years earlier.
The dorsum and tip later became crooked and were corrected once, but some deviation remained.
P/E
The "L"-shaped silicone extending to the tip was displaced to the left, and the tip and columella were also crooked.
The height and shape of the nostrils were also asymmetric.
Ear cartilage had been laid on top of the silicone that reached the tip.
OP
Through a closed approach, the silicone, capsule, and ear cartilage at the tip were removed,
and repositioning was performed to set the tip cartilages upright.

The nose became straight overall, and its height and shape also improved naturally.

The tilted columella and tip settled into a straight position.
When the deformity of the tip and columella is not severe, as in this case, a closed approach
with tip cartilage repositioning can still achieve correction.

The nose, which had looked excessively large and long, changed to a natural, well-defined appearance.


PH
Woman in her 30s. 10 years earlier, at another clinic, she had a columellar strut made of septal cartilage placed through an open approach,
along with augmentation rhinoplasty with silicone.
Something protruded at the columella, and it was corrected through a closed approach 7 years earlier, but the protrusion remained.
P/E
The dorsal silicone, tip, and columella were crooked.
The nose had shortened. (Early contracture)
OP
Through a closed approach, the silicone, capsule, and strut were removed, followed by tip cartilage repositioning.
The capsule was very thick.

Before surgery, the dorsum and tip were tilted and the outline of the silicone was clearly visible,
but both the dorsum and tip are now straight and natural.
After surgery, the nostrils are also much less visible from the front.

The tip and columella have become distinctly straight.

As the upturned tip came down, the nose lengthened and the bridge now extends in a straight line.

Before removal, the tip was upturned due to contracture; after removal, the tip came down considerably,
the nose lengthened, and the bridge is straight and well extended.
The nasolabial angle decreased by more than 10 degrees, and the tip looks more projected.
This is the result of cartilage repositioning, in which the tip cartilages that had been pulled upward are dissected free and restored to their original position;
the shape of the tip improved remarkably.

After the removal surgery, tip mobility improved greatly, and almost every movement,
including the so-called "pig nose," became possible.