

Correction of a Deviated Nose with a Dorsal Hump: A Case

A dorsal hump refers to a nose in which, around the middle of the dorsum (where bone and cartilage meet),
the framework has grown excessively, making the dorsum bulge outward.
In other words, the hump forms when bone grows excessively during adolescence in the middle of the dorsum, where the growth plate is located.
As the framework overgrows during the growth period, the left and right sides often grow at different rates,
and when the nasal bone grows faster on one side the nose becomes deviated, so a hump and a deviated nose often appear together.
In my practice, among patients who have had a dorsal hump corrected, a considerable number come to us because the nose has become too large and the tip too pointed,
making it look unnatural, and because the skin has gradually thinned so that the implant shows through.
This happens because, after the hump is rasped down with an instrument, a silicone implant is placed on the dorsum and, to match the raised dorsum,
the tip is raised as well, making the nose larger.
Key Points in Dorsal Hump Correction
01 A silicone implant should not be placed on the dorsum.
02 The nose must be examined carefully to confirm whether it is also deviated.
03 The surgery must be performed with autologous cartilage.
In the proper correction of a dorsal hump, a silicone implant should never be used, and the surgery should be performed with autologous tissue alone.
In the proper correction of a dorsal hump, the central part of the dorsum, where the hump is most pronounced, is reduced as little as possible,
and if the glabella and the tip are raised slightly, the dorsal line connects straight and the hump can be corrected.
When 2 mm or more of the hump is removed, the roof of the dorsal framework opens (open roof),
so in that case a spreader graft using septal cartilage is the most suitable option.
The reason silicone implants are so often used in dorsal hump correction is that removing a large amount of the hump raises concern about an open roof,
and, for lack of experience with the spreader grafts that can correct it, the hump is not reduced enough to make it a straight line,
and silicone ends up being inserted to cover the remaining hump.
Today, we will look at the case of a patient who had both a hump and dorsal deviation.

CC
The dorsum had a hump and deviation, there was nasal obstruction,
and, with a drooping nasal tip, the tip and columella hung down.
P/E
The dorsal deviation began where the cartilaginous part of the dorsum starts and, toward the tip,
curved progressively to the right, and the septum was also deviated in a reverse “C” shape.
OP
Hump resection, resection and repositioning of the septal cartilage (swing door),
spreader graft with septal cartilage,
and a columellar strut with ear cartilage (correcting the tip droop while raising its height)

Because of septal deviation, the end of the septum can be seen to be deviated to the left.

A
Resected septal cartilage
B
The septum positioned in the midline after the swing door procedure, which repositions the septum.
On the patient's right side, septal cartilage was added for reinforcement.
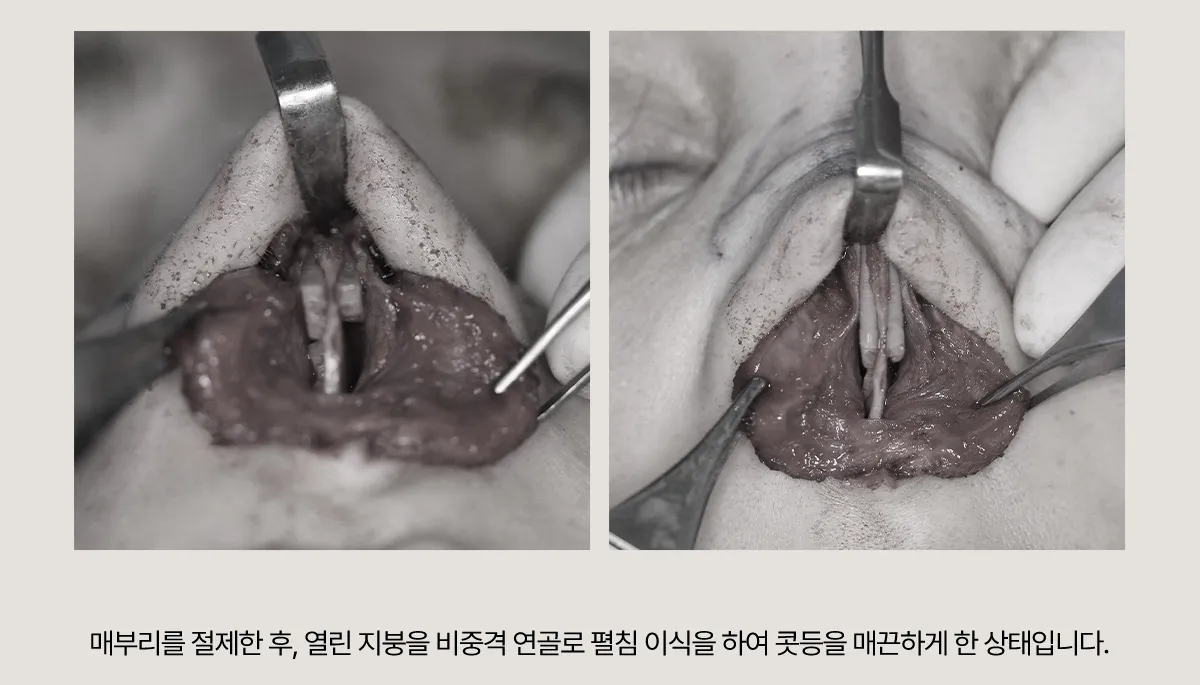
After the hump was resected, the open roof was reconstructed with a spreader graft of septal cartilage, leaving the dorsum smooth.

The nostrils, which looked like a "dragon's nose" before surgery because of the long, hanging columella,
became natural after surgery as the columella was raised.

Before surgery the columella was tilted and the nostrils were asymmetric,
but after surgery the nostrils became slender and symmetric.

The dorsal line became straight and well defined.

The humped dorsal line became smooth, and as the long, drooping tip was lifted and defined,
the drooping nasal tip was corrected as well.
